متلازمة وولف-باركنسون-وايت
مراجعة من قبل الدكتور أدريان بونسال، بكالوريوس الطب والجراحةآخر تحديث بواسطة الدكتور كولين تايدي، MRCGPآخر تحديث 1 أغسطس 2017
يتوافق مع الإرشادات التحريرية
- تنزيلتنزيل
- مشاركة
- Language
- نقاش
- Ask Patient
- نسخة صوتية
- أضف إلى المصادر المفضلة على جوجل
في هذه السلسلة:خفقان القلببطء القلباضطرابات نظم القلبتسرع القلب فوق البطيني
تنويه بشأن المحتوى
لم تتم مراجعة هذه الصفحة مؤخرًا، لذا ربما تكون بعض المعلومات أو الروابط الخارجية قد تغيّرت.
متلازمة وولف-باركنسون-وايت ليست شائعة ولكنها يمكن أن تسبب سرعة في ضربات القلب أو اضطرابات أخرى في نظم القلب من وقت لآخر. يمكن تقديم العلاج لسرعة ضربات القلب وأيضًا لمنع أي نوبات أخرى.
نظرة سريعة
Wolff-Parkinson-White syndrome is a heart condition present from birth.
It involves an extra electrical connection in the heart, disrupting normal electrical activity.
This can lead to episodes of a very fast heart rate, causing palpitations, dizziness, or chest pain.
Diagnosis often involves an ECG, which shows classic changes.
Treatment can include simple measures, medicines, or a procedure called radiofrequency ablation.
Radiofrequency ablation can often cure the condition.
What is Wolff-Parkinson-White syndrome?
In Wolff-Parkinson-White (WPW) syndrome there is an extra connection (an accessory pathway) between the atria and ventricles. This means that as well as electrical impulses passing normally between the atria and the ventricles at the AV node, electrical impulses can also pass abnormally along the accessory pathway.
The accessory pathway in WPW syndrome is known as the bundle of Kent. It is a congenital problem which means that it is present from birth. The majority of people with WPW syndrome have no other heart abnormalities.
An electrical impulse that passes along the accessory pathway can arrive at the ventricles more quickly than normal. There is not the usual impulse delay that occurs at the AV node and no limiting of the electrical impulses that pass through. This can cause the heart rate to speed up. The accessory pathway can also sometimes transmit electrical impulses backwards from the ventricles to the atria.
So, in WPW syndrome, the normal electrical activity of the heart is disrupted. There is a risk of developing a fast heart rate (a tachycardia) from time to time and other heart rhythm disturbances (arrhythmias). WPW syndrome can lead to what is called a supraventricular tachycardia. Tachycardia is a heart rate over 100 beats per minute (bpm). 'Supra' means above and because the atria are above the ventricles, the tachycardia is supraventricular.
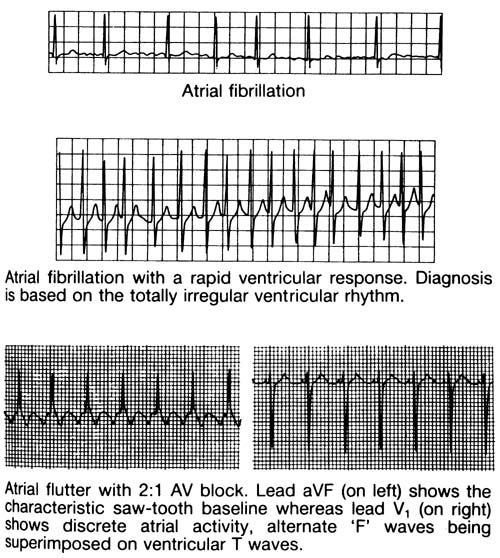
The common arrhythmia that occurs in WPW syndrome is a paroxysmal (intermittent) supraventricular tachycardia (SVT). Other arrhythmias that can also occur include الرجفان الأذيني (AF), atrial flutter and atrioventricular re-entrant tachycardia (AVRT). Rarely, another arrhythmia called ventricular fibrillation can develop.
How common is Wolff-Parkinson-White syndrome?
WPW syndrome probably affects somewhere between 1-3 in 1,000 people. It is more common in men. There does seem to be some genetic basis, as WPW syndrome can run in families. However, most cases of WPW syndrome occur in people with no known family history.
الأعراض
Symptoms are caused by the episodes of rapid heart rate (tachycardia). How often these episodes occur can vary from person to person. They can include:
In some people, symptoms can be more severe. An episode of a very rapid heart rate (up to about 250 bpm) can cause:
Your blood pressure to drop and lead to collapse (blackout).
A build-up of fluid in your lungs and ضيق في التنفس.
Your heart can stop beating altogether (a cardiac arrest). However, this is rare.
In some people, the rapid heart rate only ever occurs once or twice. In others, it can occur a few times per week. Each episode of tachycardia may last from less than a minute to a few hours. An episode of tachycardia may even last for a few days but this is rare.
Many people are not aware that they have WPW syndrome because their symptoms are mild or don't occur very often.
How is Wolff-Parkinson-White syndrome diagnosed?
It may be diagnosed by doing a تخطيط القلب (تخطيط كهربية القلب، أو ECG). There are classic changes on the ECG that can be seen in some people with WPW syndrome.
أحيانًا يكون تخطيط القلب المتنقل may be suggested.
Special tests called electrophysiology studies may be carried out in some people. They can help to find the precise area in the heart where the accessory pathway is located.
العلاج
Treating an episode of rapid heart rate
Many episodes of SVT soon stop on their own and no treatment is needed.
Simple measures, including drinking a cold glass of water, holding your breath or putting your face into cold water.
If an episode of SVT lasts a long time or is severe, you may need to be admitted to hospital.
Medicines can be used to stop an episode of SVT - eg, adenosine.
Electric shock treatment (cardioversion) is sometimes used.
Prevention of episodes of rapid heart rate
If you have no symptoms and are at low risk of complications you may need no treatment.
Radiofrequency destruction (ablation) is the treatment of choice but other options are available.
الاستئصال بالترددات الراديوية
A thin tube called a catheter is inserted into an artery near your groin. The tube is passed up to your heart.
The small area in your heart that causes the fast heart rate (the accessory pathway) is destroyed using a type of energy called radiofrequency.
Radiofrequency ablation can have very good results and can cure the condition in most people.
Medication treatment
Long-term treatment with a medicine may be advised if you don't want to have radiofrequency ablation, or if this has failed. One medicine used is called amiodarone.
Heart surgery
Heart surgery is still used in some cases - eg, if radiofrequency ablation has failed and you don't want to take medication for the rest of your life. Open heart surgery aims to find and destroy the accessory pathway that causes the fast heart rate.
ما هي التوقعات؟
WPW syndrome can be life-threatening during an acute episode of SVT but the outlook (prognosis) is otherwise very good. Catheter ablation usually cures WPW syndrome but some people with WPW aren't suitable for this treatment.
اختيارات المرضى لـ خفقان القلب
صحة القلب والأوعية الدموية
الرجفان الأذيني
الرجفان الأذيني (AF) هو نبض قلب سريع وغير منتظم بشكل غير طبيعي. يُطلق على إيقاع ضربات القلب غير الطبيعي اسم اضطراب النظم. يكون معدل ضربات القلب الطبيعي بين 60 و100 نبضة في الدقيقة (نبضة في الدقيقة) عندما تكون في حالة راحة. في حالة الرجفان الأذيني، يمكن أن يكون معدل ضربات القلب سريعًا جدًا (غالبًا بين 140 و180 نبضة في الدقيقة) بالإضافة إلى كونه غير منتظم.
بقلم الدكتور دوغ مكيتشني، MRCGP

صحة القلب والأوعية الدموية
خفقان القلب
خفقان القلب هو الشعور بنبض قلبك وهو شائع. معظم الحالات غير ضارة. عادة ما تستمر لفترة قصيرة فقط ويمكن أن تصاحبها أعراض أخرى مثل ضيق التنفس، الدوخة، ضيق الصدر والشعور بالقلق. الخفقان الشديد أو الذي لا يهدأ بسرعة قد يحتاج إلى عناية طبية عاجلة. الأسباب الأكثر شيوعًا مذكورة أدناه.
بقلم الدكتورة هايلي ويلاسي، FRCGP
الأسئلة الشائعة
Can Wolff-Parkinson-White syndrome develop later in life?
No, Wolff-Parkinson-White (WPW) syndrome is a congenital condition, meaning it is present from birth. It is caused by an extra electrical connection in the heart called the bundle of Kent, which forms during foetal development.
If WPW syndrome is congenital, why might symptoms only appear later in adulthood?
While WPW syndrome is present from birth, many people are not aware they have it because their symptoms are mild or do not occur very often. Symptoms, which are caused by episodes of a rapid heart rate, can vary greatly in how frequently they happen, from rarely to several times a week. This means that for some, the condition might only become noticeable or diagnosed later in life when symptoms become more prominent or frequent.
Are there different types of accessory pathways in WPW syndrome?
The specific extra connection seen in Wolff-Parkinson-White syndrome is known as the bundle of Kent. While there may be variations in its exact location or electrical properties, the presence of this particular accessory pathway is what defines WPW syndrome.
Is it possible to have Wolff-Parkinson-White syndrome and other heart conditions?
The majority of people with Wolff-Parkinson-White syndrome do not have any other heart abnormalities. However, the article does not rule out the possibility entirely, only stating that most cases do not involve additional heart issues.
Can lifestyle changes help manage WPW syndrome?
The article suggests simple measures like drinking a cold glass of water, holding your breath, or putting your face into cold water can sometimes help stop an episode of rapid heart rate. However, it does not discuss broader lifestyle changes beyond these immediate responses to an acute episode.
If I have WPW syndrome, will my children also have it?
There does appear to be some genetic basis for Wolff-Parkinson-White syndrome, as it can run in families. However, most cases occur in people with no known family history. This suggests a potential for inherited risk, but it's not a certainty.
How long do the effects of radiofrequency ablation last?
Radiofrequency ablation can have very good results and can cure Wolff-Parkinson-White syndrome in most people. This implies a long-lasting or permanent resolution of the condition for those successfully treated.
قراءة إضافية ومراجع
- Symptoms, Diagnosis and Monitoring of Arrhythmias; American Heart Association, 2009
- Kireyev D, Fernandez SF, Gupta V, et al; Targeting tachycardia: diagnostic tips and tools. J Fam Pract. 2012 May;61(5):258-63.
- Camm AJ; Cardiac arrhythmias--trials and tribulations. Lancet. 2012 Oct 27;380(9852):1448-51. doi: 10.1016/S0140-6736(12)61773-5.
- Raviele A, Giada F, Bergfeldt L, et al; Management of patients with palpitations: a position paper from the European Heart Rhythm Association. Europace. 2011 Jul;13(7):920-34. doi: 10.1093/europace/eur130.
- فحص نبضك; مؤسسة القلب البريطانية
- Sohinki D, Obel OA; Current trends in supraventricular tachycardia management. Ochsner J. 2014 Winter;14(4):586-95.
- Albert CM, Stevenson WG; مستقبل اضطرابات النظم الكهربائي وعلم الفيزيولوجيا الكهربائية. الدوران. 21 يونيو 2016;133(25):2687-96. doi: 10.1161/CIRCULATIONAHA.116.023519.
عن المؤلفعرض السيرة الذاتية الكاملة
تم التحديث بواسطة

الدكتور كولين تايدي، MRCGP
طبيب عام، مؤلف طبي
MBBS, MRCGP, MRCP (Paediatrics), DCH
الدكتور كولين تايدي هو طبيب في هيئة الخدمات الصحية الوطنية، ويعمل في أوكسفوردشاير.
حول المراجععرض السيرة الذاتية الكاملة

الدكتور أدريان بونسال، بكالوريوس الطب والجراحة
مؤلف طبي
ماجستير (كيمياء)، بكالوريوس الطب والجراحة (مع مرتبة الشرف)، دبلوم صحة الطفل
منذ عام 2000، يعمل أدريان في طب الأطفال الطارئ والرعاية الحرجة في سيدني، مع اهتمام خاص بعلم السموم، والصدمات، والإنعاش.
تاريخ المقال
المقال متاح أيضًا باللغة الإنجليزية, الألمانية, إسبانية, الفرنسية, إيطالي, البرتغالية, الهندية, العبرية, العربية ,، و السويدية.
1 أغسطس 2017 | أحدث إصدار
آخر تحديث بواسطة
الدكتور كولين تايدي، MRCGPمراجعة من قبل
الدكتور أدريان بونسال، بكالوريوس الطب والجراحة
المهنيين الطبيين
Looking for more in-depth clinical detail? Our Professional Reference articles are written for doctors, nurses and other healthcare professionals. They include comprehensive clinical guidance, diagnostic information and UK/European evidence summaries. If you need the clinical version, you can read the Professional Reference article on this topic.
شارك أفكارك أو تجاربك مع الآخرين في مجتمعات المرضى.
وصول بسيط إلى العلاجات والخدمات الصحية الموثوقة عبر الإنترنت.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.
 التهاب الجيوب الأنفية الحاد
 التهاب اللوزتين البكتيري
 القوباء
 لدغات الحشرات
 الحزام الناريعدوى المسالك البولية
اشترك في النشرة الإخبارية للمرضى
جرعتك الأسبوعية من النصائح الصحية الواضحة والموثوقة - مكتوبة لمساعدتك على الشعور بالاطلاع والثقة والتحكم.
من خلال الاشتراك، فإنك تقبل سياسة الخصوصية. يمكنك إلغاء الاشتراك في أي وقت. نحن لا نبيع بياناتك أبدًا.