الأكزيما القرصية (النملية)
مراجعة من قبل الدكتورة فيليبا فينسنت، MRCGPآخر تحديث بواسطة الدكتورة توني هازيل، زميلة الكلية الملكية للأطباء العامينآخر تحديث ٢ يونيو ٢٠٢٣
يتوافق مع الإرشادات التحريرية
- تنزيلتنزيل
- مشاركة
- Language
- نقاش
- Ask Patient
- نسخة صوتية
- أضف إلى المصادر المفضلة على جوجل
المهنيين الطبيين
تم تصميم مقالات المراجع المهنية لاستخدامها من قبل المتخصصين في الرعاية الصحية. يتم كتابتها بواسطة أطباء من المملكة المتحدة وتستند إلى أدلة بحثية وإرشادات المملكة المتحدة وأوروبا. قد تجد الأكزيما القرصية مقالة أكثر فائدة، أو واحدة من مقالاتنا الأخرى مقالاتنا الصحية.
الخلفية
The term nummular means coin-shaped, so both terms describe the characteristic round (or oval) erythematous skin plaques.
This is purely a dermatological condition that does not affect other systems. Infection is common but is secondary rather than causative.
علم الأوبئة1
The prevalence is around 2 per 1,000 people. It is more common in men than in women. There is a peak incidence in both males and females of around 50-65 years of age and a second peak in women of around 15-25 years of age. It is rare in children.
العوامل المهيئة
There may be a past history of atopic eczema and dry or sensitive skin.
عرض
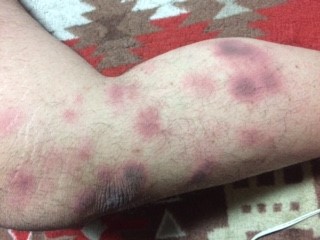
There are characteristic round or oval erythematous plaques. They are most often on the extremities, especially the legs. However, they may occur anywhere on the trunk, hands, or feet. The face and scalp are not involved. Lesions are often symmetrical.
The lesions start as erythematous or violaceous papules or vesicles. They coalesce to form confluent plaques.
Erosions may appear over the lesions due to excoriation, as itch is intense.
Early lesions, especially vesicles, often have staphylococcal infection, which produces a yellowish crust. Gross infection, with cellulitis surrounding the plaques, requires oral antibiotics.
After a few days, plaques become dry, scaly and more violaceous, particularly when below the knee. The lesions then flatten to macules, usually with brown hyperpigmentation from the inflammation. It gradually lightens but the pigment may never completely fade, particularly below the knee.
Plaques may clear in the centre and resemble tinea corporis.
The condition varies in intensity rather than being constant.
The eruptions are intensely itchy but they may also burn or sting. Pruritus is always worst at night, almost irrespective of the aetiology.
There tends to be seasonal variation in intensity. It is worse in cold and dry weather and better in warm and humid conditions.
Chronic changes on the skin of the legs due to discoid (nummular) eczema
التشخيص التفريقي
تينيا الجسم usually has few vesicles, a raised narrow border and scale on the outside of the plaque.
Other forms of dermatitis, including asteatotic eczema و التهاب الجلد التأتبي, are very similar but fortunately treatment is similar.
التهاب الجلد التماسي may show a pattern from the offending agent.
Lichen simplex chronicus often occurs on the lower legs, the neck, the scalp, or the scrotum. It is lichenified or thickened by chronic scratching, more violaceous and, often, has no clear border.
Stasis dermatitis may occur simultaneously on the lower extremities and venous stasis may lead to the development of both conditions.
Plaques of psoriasis are often found on the extensor surfaces, especially at the elbows and knees and the scalp is often involved. The scale is usually thick and silver.
التحقيقات2
Scrapings of lesions are commonly analysed to exclude tinea.
If there is secondary infection, swabs should be taken.
Patch testing may be useful to exclude other causes in severe or persistent cases.
Biopsy is not usually required.
الأمراض المرتبطة
Most patients with discoid eczema have dry sensitive skin. The cause of the condition is unknown but irritation from insect bites, chemicals or abrasions may be involved. Venous insufficiency and stasis may aggravate the condition on the lower legs. Severe discoid eczema has been reported after administration of interferon and ribavirin for hepatitis C.3
الإدارة4
The basic components of treatment are:
Rehydration of the skin.
Treating infection.
تقليل الالتهاب.
Patients should shower or bathe once or twice a day in cool water. Moisturisers or medicated topical preparations should be used to seal the water in the skin.
If medication is applied to damp skin it helps seal it and aids penetration.
Topical steroids reduce inflammation. Usually mild ones are adequate but, in severe disease, stronger steroid applications may be required and, in very severe cases, oral steroids can be needed. Ointments tend to be more effective than creams. The effect of topical applications can be enhanced by occlusion or by applying ointment on wet skin that has been soaking and has not been dried.5
If there is secondary infection then antibiotics are required. Oral antibiotics, effective against staphylococci and streptococci, should be used.
Antihistamines can reduce pruritus and aid sleep. As the pruritus is not a direct effect of histamine, the sedative effect is more important than the antihistamine action and so the older, sedating ones are needed. A higher dose at night will aid sleep.
Tar preparations may reduce inflammation, particularly in older, thickened, scaly plaques.
After the eruption has resolved, continue aggressive hydration to reduce the frequency of attacks, especially in dry climates. Moisturisers for sensitive skin may be applied or petroleum jelly applied to damp skin after showering.
Resting in a cool, moist environment helps, whilst a hot dry environment aggravates the problem.
Sunlight or phototherapy may benefit chronic cases. Ultraviolet radiation helps reduce the inflammatory activity within the skin but there is risk of heat worsening the pruritus and ultraviolet light has its own problems, including carcinogenesis.
In severe cases, immunosuppressant drugs such as methotrexate, azathioprine or ciclosporin may be used. 2
المضاعفات
Secondary infection may occur.
Excoriation or infection may leave permanent scars.
Lesions on the lower extremities are slow to heal and may leave permanent brown macules.
التكهن
It tends to be a chronic and recurrent disease. Attention to features that reduce relapse will make life more tolerable.
Reducing relapse
Use moisturisers freely to keep the skin well hydrated.
Avoid hot baths but cool or lukewarm ones are permissible. Do not use soap. Oils may be added to the bath.
After a bath or shower, pat the skin dry and apply an emollient.
Wear loose clothes of materials that do not irritate.
A room humidifier may help, especially with central heating or air conditioning.
تحديثات حصرية لمتخصصي الرعاية الصحية
ابقَ على اطلاع بأحدث التحديثات السريرية، والرؤى المهنية، والإرشادات المستندة إلى الأدلة. تقوم نشرة Patient Pro الإخبارية بتجميع محتوى أساسي لمتخصصي الرعاية الصحية - يتم تسليمه مباشرة إلى بريدك الوارد.
من خلال الاشتراك، فإنك تقبل سياسة الخصوصية. يمكنك إلغاء الاشتراك في أي وقت. نحن لا نبيع بياناتك أبدًا.
قراءة إضافية ومراجع
- Eczema: discoid (syn. nummular) eczema; Primary care dermatology society, May 2022
- Burgin S, Nummular Eczema, Lichen Simplex Chronicus, and Prurigo Nodularis, Fitzpatrick's Dermatology in General Medicine, Eighth Edition, 2012.
- الأكزيما القرصية; ديرم نت نيوزيلندا
- Hashimoto Y, Kanto H, Itoh M; Adverse skin reactions due to pegylated interferon alpha 2b plus ribavirin combination therapy in a patient with chronic hepatitis C virus. J Dermatol. 2007 Aug;34(8):577-82.
- Lebwohl M et al; Treatment of Skin Disease: Comprehensive Therapeutic Strategies, 2013.
- Gutman AB, Kligman AM, Sciacca J, et al; Soak and smear: a standard technique revisited. Arch Dermatol. 2005 Dec;141(12):1556-9.
عن المؤلفعرض السيرة الذاتية الكاملة
تم التحديث بواسطة

Dr Toni Hazell, FRCGP
بكالوريوس الطب والجراحة، بكالوريوس العلوم، زميل الكلية الملكية للأطباء العامين، دبلوم في الصحة الجنسية والإنجابية، دبلوم في طب الجهاز البولي التناسلي، دبلوم الكلية الملكية لأطباء النساء والتوليد، دبلوم في صحة الطفل (لندن، المملكة المتحدة، 2000)
تخرجت الدكتورة توني هازيل من كلية الطب بمستشفى سانت ماري وأكملت تدريبها في مستشفى نورثويك بارك.
حول المراجععرض السيرة الذاتية الكاملة

الدكتورة فيليبا فينسنت، MRCGP
طبيب عام، مؤلف طبي
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
الدكتورة فيليبا فينسنت هو طبيب عام في هيئة الخدمات الصحية الوطنية يعمل في شمال لندن.
تاريخ المقال
المقال متاح أيضًا باللغة الإنجليزية, الألمانية, إسبانية, الفرنسية, إيطالي, البرتغالية, الهندية, العبرية, العربية ,، و السويدية.
المراجعة التالية مستحقة: 12 مايو 2028
٢ يونيو ٢٠٢٣ | أحدث إصدار
وصول بسيط إلى العلاجات والخدمات الصحية الموثوقة عبر الإنترنت.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.
 التهاب الجيوب الأنفية الحاد
 التهاب اللوزتين البكتيري
 القوباء
 لدغات الحشرات
 الحزام الناريعدوى المسالك البولية